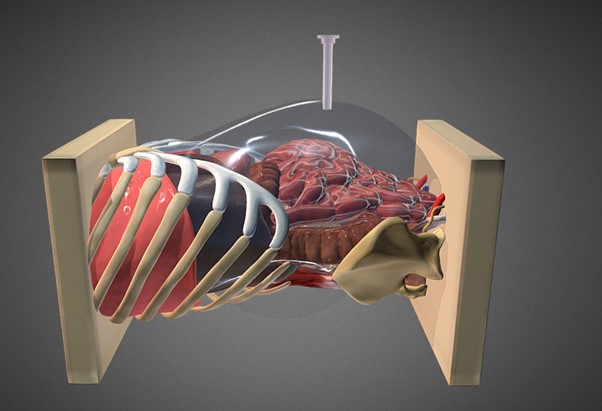
Although the technique of complete ‘soft tissue’ pelvic exenteration, involving en bloc resection of the rectum and genitourinary organs, has been refined and improved since first described by Alexander Brunschwig now 75 years ago, the principles remain broadly the same and largely reflect the simpler end of the spectrum of technical exenterative surgery1. The periphery of the pelvis and the “extra TME” plane is like a busy freeway intersection wrapped in an igloo of bone limiting access and control, and is where major technical advances have been made since the turn of the century. These technical approaches have been driven by individual patient anatomy and pathology and the determinant that more radical approaches to obtain an R0 margin result in better survival and quality of life. The development of techniques for en bloc bone and neurovascular resection have seen exenteration surgery evolve beyond a uniform procedure of the central compartment, to a bespoke and dynamic operation for which the technical approach varies based on the anatomy of the tumour. These advances have allowed safe and oncologically complete resection of higher and wider tumours which were previously considered unresectable and have dramatically changed the indications of what were previously deemed incurable and unresectable.
By definition, pelvic exenteration surgery for locally advanced primary or recurrent rectal cancer requires dissection beyond the traditional total mesorectal excision (TME) plane in order to achieve en bloc resection of the tumour and all involved adjacent pelvic organs, bone and soft tissue structures. These extra-TME tumours require extra-TME surgery and historically have not been taught during regular fellowship surgical training. Dissection planes may be distorted or obliterated secondary to previous surgery, radiotherapy and/or sepsis, particularly in recurrent disease. Understanding these concepts as well as the five anatomical compartments of the pelvis (central, anterior, left and right lateral, posterior) is to understand the anatomical and technical basis of exenterative surgery2. The exenteration surgeon must be confident dissecting all the pelvic compartments involved when planned, based on preoperative imaging, but also when unanticipated, i.e. when deviation from the planned extent of surgery is necessary due to unexpected intraoperative findings such as tumour extension or bleeding.
The series of technical videos presented in BJS demonstrate the radical extra-TME techniques developed at Royal Prince Alfred Hospital, and based on an experience of now well over 1000 pelvic exenterations. Each of these educational videos has been created with input from fellows who train in exenteration surgery at our centre and learn these techniques with the view to adopting them in their own units around the world. The techniques presented for anterior compartment tumours include composite pubic bone resection, perineal urethrectomy for the male patient and inter-labial vaginectomy for the female patient. In the posterior compartment, abdominolithotomy sacrectomy is described. This technique is used routinely when low sacrectomy (below the S2/3 junction) is required, and is increasingly used for tumours involving the central high sacrum (between neural foramina), where the anterior cortex of the sacrum of S1 and/or S2 is excised followed by full thickness sacral transection at S3. This avoids the need for a traditional prone phase and additional sacral skin incision. Lateral compartment excision is demonstrated, including en bloc resection of the internal iliac vascular system and exposure of the lumbosacral trunk and sacral nerve roots becoming confluent to form the sciatic nerve as they exit the pelvis behind the ischial spine. The aim of the series was to present the key techniques our fellows are exposed to and make the educational experience accessible for other exenteration surgeons around the globe.
References
Brown KGM, Solomon MJ, Koh CE. Pelvic Exenteration Surgery: The Evolution of Radical Surgical Techniques for Advanced and Recurrent Pelvic Malignancy. Dis Colon Rectum. 2017;60(7):745-54.
van Kessel CS, Solomon MJ. Understanding the Philosophy, Anatomy, and Surgery of the Extra-TME Plane of Locally Advanced and Locally Recurrent Rectal Cancer; Single Institution Experience with International Benchmarking. Cancers (Basel). 2022;14(20).